Temple Fat Grafting
qd Temple Fat Grafting
Temple hollows are assessed along the transition between the outer forehead and cheekbone. Differences in tissue volume, muscle movement and the two sides guide planning.
Temple Fat Grafting is available at QD Clinic in Gangnam, Seoul, Korea.

is this for me
Who it’s for
Even if none of these describes you, we will look again at the consultation.
- People seeking assessment of a local hollow that may reflect soft-tissue volume loss
- People able to plan recovery and follow-up for both the face and donor area
- People who understand partial absorption, asymmetry and the possibility of further correction
Filling a temple does not narrow the cheekbone or reduce jaw muscle size. Equal quantities on both sides are not automatically appropriate.
start with your concern
Before you pick a treatment name, start with the cause of your concern.
Even a treatment with the same name takes on a different role and scope depending on your current structure, the change you want, what you have had before and the recovery time you have.
Area and cause
The surgeon examines soft-tissue loss, temporalis movement and skeletal differences. Prior lifting or grafting and the contact points of spectacle arms are reviewed.
Scope and limitations
Filling a temple does not narrow the cheekbone or reduce jaw muscle size. Equal quantities on both sides are not automatically appropriate.
Follow-up
Avoid sustained temple pressure from glasses or side sleeping as instructed. Report marked pain, skin-colour changes or persistent chewing discomfort.
the principle
How it works
Temple Fat Grafting
Temple hollows are assessed along the transition between the outer forehead and cheekbone. Differences in tissue volume, muscle movement and the two sides guide planning. Autologous fat grafting transfers prepared fat from a donor area, such as the abdomen or thighs, to supplement soft-tissue volume. The graft needs to establish a blood supply, and some fat may be absorbed. Retention and contour vary; a fixed survival rate or permanently unchanged shape cannot be promised. Filling a temple does not narrow the cheekbone or reduce jaw muscle size. Equal quantities on both sides are not automatically appropriate.
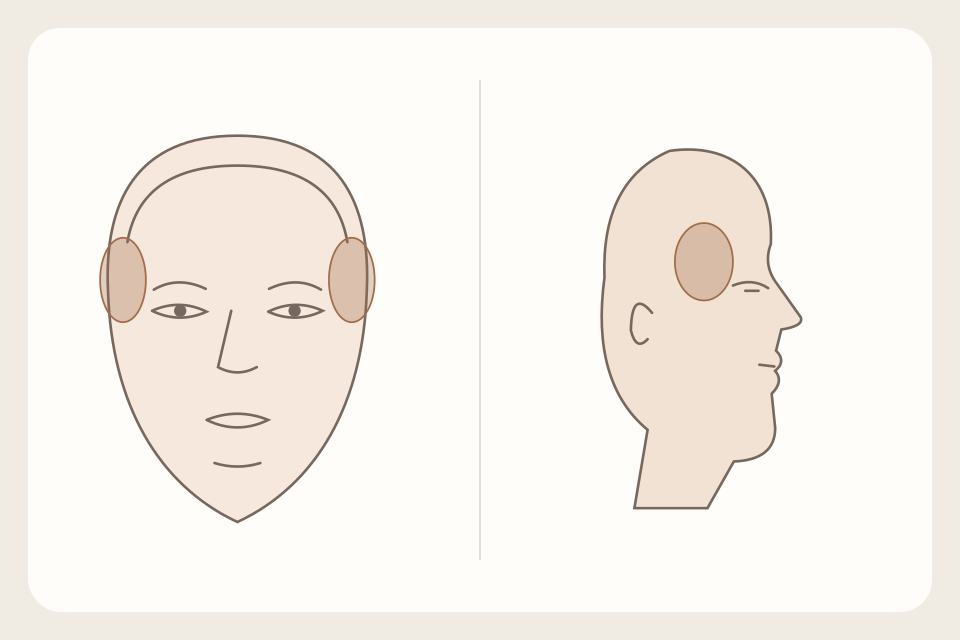
How it works
Area and cause
The surgeon examines soft-tissue loss, temporalis movement and skeletal differences. Prior lifting or grafting and the contact points of spectacle arms are reviewed.
Harvest and preparation
The surgeon assesses donor fat and skin, then plans anaesthesia and harvesting. The harvested fat is prepared, and wound care and recovery at the donor site are explained alongside facial recovery.
Placement and review
Placement is distributed according to tissue thickness and local vascular and nerve anatomy. Excessive filling in one session is avoided, and any further correction is considered after swelling and absorption have been reviewed.
the qd standard
The same treatment, never the same plan.
Rather than a fashionable name or a fixed package, we weigh the structure found at examination, safety, recovery and the limits within one plan.
- DIAGNOSIS FIRST
Cause before name
We first separate out the tissue and the function behind your concern.
- LESS, PRECISE
Only as much as needed
Rather than an excessive change, we plan the smallest scope with a clear role.
- HONEST LIMIT
The limits, explained too
We explain the change you can expect, the alternatives, individual differences and the risks.
personal plan
From consultation to follow-up, planned as one flow.
Temple hollows are assessed along the transition between the outer forehead and cheekbone. Differences in tissue volume, muscle movement and the two sides guide planning.


Area and cause
The surgeon examines soft-tissue loss, temporalis movement and skeletal differences. Prior lifting or grafting and the contact points of spectacle arms are reviewed.
Harvest and preparation
The surgeon assesses donor fat and skin, then plans anaesthesia and harvesting. The harvested fat is prepared, and wound care and recovery at the donor site are explained alongside facial recovery.
Placement and review
Placement is distributed according to tissue thickness and local vascular and nerve anatomy. Excessive filling in one session is avoided, and any further correction is considered after swelling and absorption have been reviewed.
What the procedure is like
- The surgeon examines soft-tissue loss, temporalis movement and skeletal differences. Prior lifting or grafting and the contact points of spectacle arms are reviewed.
- The surgeon assesses donor fat and skin, then plans anaesthesia and harvesting. The harvested fat is prepared, and wound care and recovery at the donor site are explained alongside facial recovery.
- Placement is distributed according to tissue thickness and local vascular and nerve anatomy. Excessive filling in one session is avoided, and any further correction is considered after swelling and absorption have been reviewed.
Anaesthesia and duration are planned after assessment of the recipient areas, donor site and health. Arrange transport home and early follow-up before surgery.
Please read this before treatment
- Avoid sustained temple pressure from glasses or side sleeping as instructed. Report marked pain, skin-colour changes or persistent chewing discomfort.
- Avoid firm pressure or rubbing over the graft. Follow individual advice on washing, sleep position and exercise, and check whether donor-site dressings or compression are needed.
Safety & considerations
Possible complications
- Swelling, bruising, pain, bleeding, infection, scarring or altered sensation can affect the face and donor area.
- Absorption, asymmetry, overcorrection, undercorrection, irregularity, nodules, fat necrosis or oil cysts may occur.
- Rare vascular complications can cause skin injury, visual loss or neurological injury; anatomical assessment is essential.
Before surgery
- Describe previous fillers, fat transfer, implants and facial operations, including dates, locations and materials.
- Report medicines, supplements, allergies, bleeding conditions, smoking and recent weight changes; do not stop prescribed medicine yourself.
Sudden visual changes, severe pain, pale or dark skin, difficulty speaking or limb weakness require emergency assessment. Rapidly increasing swelling, fever or discharge also need prompt medical review.
what to expect
What to expect over time
A general guide to how the days and months after treatment usually unfold. Results vary by individual.
Early care
Avoid firm pressure or rubbing over the graft. Follow individual advice on washing, sleep position and exercise, and check whether donor-site dressings or compression are needed.
Follow-up
Facial swelling, colour and texture are reviewed together with donor-site wounds. Early asymmetry is not automatically the final outcome, but sudden pain or colour change must not wait.
Contour assessment
Volume is reassessed with photographs and examination over the months in which swelling and absorption settle. Remaining hollows and tissue condition guide whether and when another graft is appropriate.
Sessions & results
Avoid sustained temple pressure from glasses or side sleeping as instructed. Report marked pain, skin-colour changes or persistent chewing discomfort. Volume is reassessed with photographs and examination over the months in which swelling and absorption settle. Remaining hollows and tissue condition guide whether and when another graft is appropriate.
how it compares
How it compares
Filling a temple does not narrow the cheekbone or reduce jaw muscle size. Equal quantities on both sides are not automatically appropriate.
| Temple Fat Grafting | Hyaluronic acid filler | |
|---|---|---|
| Scope and limitations | Autologous fat grafting transfers prepared fat from a donor area, such as the abdomen or thighs, to supplement soft-tissue volume. The graft needs to establish a blood supply, and some fat may be absorbed. Retention and contour vary; a fixed survival rate or permanently unchanged shape cannot be promised. | A manufactured gel adds local volume without fat harvesting. Suitability and duration depend on the product and area, and vascular complications remain possible. Equivalent amounts or recovery cannot be assumed. |
before consultation
Before you decide, the questions people always ask
Reducing a hollow can soften the contrast between a temple and cheekbone. It does not reduce the width or projection of the cheekbone itself. Assessment identifies whether volume loss or skeletal prominence is the main concern. Overfilling a temple to disguise bone width is avoided.
Bone shape and temporalis thickness can contribute to the difference. The temples are assessed at rest and during gentle jaw movement. Each side may need a different plan; equal amounts do not guarantee equal contours. Structural asymmetry and differences in fat retention may remain after recovery.
The pressure from the spectacle arms and their relationship to access sites matter. Discuss a way to limit prolonged compression or rubbing during early healing. Deep marks or pain from the frame should be reviewed rather than tolerated. Bring your usual glasses to the consultation if you depend on them for vision.
Earlier lifting or other surgery can change tissue planes and create adhesions. Provide the date, technique, incision location and any residual sensory symptoms. A scar alone does not establish suitability; skin and deeper tissue need examination. Records can help determine whether the area or approach should be limited.
Related surgeries
 Fat grafting
Forehead Fat Grafting
qd Forehead Fat GraftingOwn fat may supplement a flat or locally hollow forehead. Assessment considers frontal symmetry, the profile curve and the transition from the brows to the hairline. Fat grafting
Anterior Cheek Fat Grafting
qd Anterior Cheek Fat GraftingThe anterior cheek below the eye is assessed for forward volume and its transition into the lower eyelid and nasolabial area. Facial expression is considered alongside resting shape. Fat grafting
Lateral Cheek Fat Grafting
qd Lateral Cheek Fat GraftingLocal hollows beneath the cheekbone and along the side of the face may be supplemented with own fat. Skin laxity, facial width and recent weight changes affect the plan. Fat grafting
Under-Eye Fat Grafting
qd Under-Eye Fat GraftingThe tear trough and lower-eyelid-to-cheek transition are checked for a true volume deficit. Thin skin, protruding fat, swelling and pigmentation are distinguished before grafting is considered. Fat grafting
Nasolabial Fold Fat Grafting
qd Nasolabial Fold Fat GraftingHollowing and skin folding between the nostril and mouth are assessed separately. The plan considers volume support, facial movement and descent of the midface. Fat grafting
Chin Fat Grafting
qd Chin Fat GraftingSoft-tissue deficiency at the chin and the transition from the lower lip are assessed. Profile projection, frontal width and symmetry guide the scope of fat transfer.

personal consultation
Tell us what bothers you now, the change you want, what you have had done before and any dates that matter. We will compare the possible approaches and their limits, calmly.
Consult now